A breast cancer report that says ER positive or PR positive can raise many questions at once.
Hormone receptor positive breast cancer is the most common form of the disease, and it also has some of the most effective treatment options, because its dependence on hormones gives doctors a way to slow or block its growth. Understanding what the result means, how treatment is built, and what shapes the outlook can help patients take part confidently in decisions. This guide, reviewed by
Renova's medical oncology team, explains hormone receptor positive breast cancer in clear, practical terms.
Key Takeaways
- Hormone receptor positive means the cancer cells have receptors for oestrogen (ER), progesterone (PR), or both.
- It is the most common type of breast cancer, commonly cited as roughly 70 to 80 percent of cases.
- Receptor status is confirmed on the biopsy or surgical specimen and guides treatment from the start.
- Hormone (endocrine) therapy is a cornerstone of treatment and is often taken for five to ten years.
- Surgery, radiation, chemotherapy, and targeted therapy are added according to stage and tumour features.
- Outlook is often favourable, especially when found early, but depends on stage, grade, node involvement, and HER2 status.
- Staying on hormone therapy as prescribed matters, because stopping early can raise the risk of recurrence.
- Late recurrence can occur, so long-term follow-up is part of care.
What Does Hormone Receptor Positive Mean?
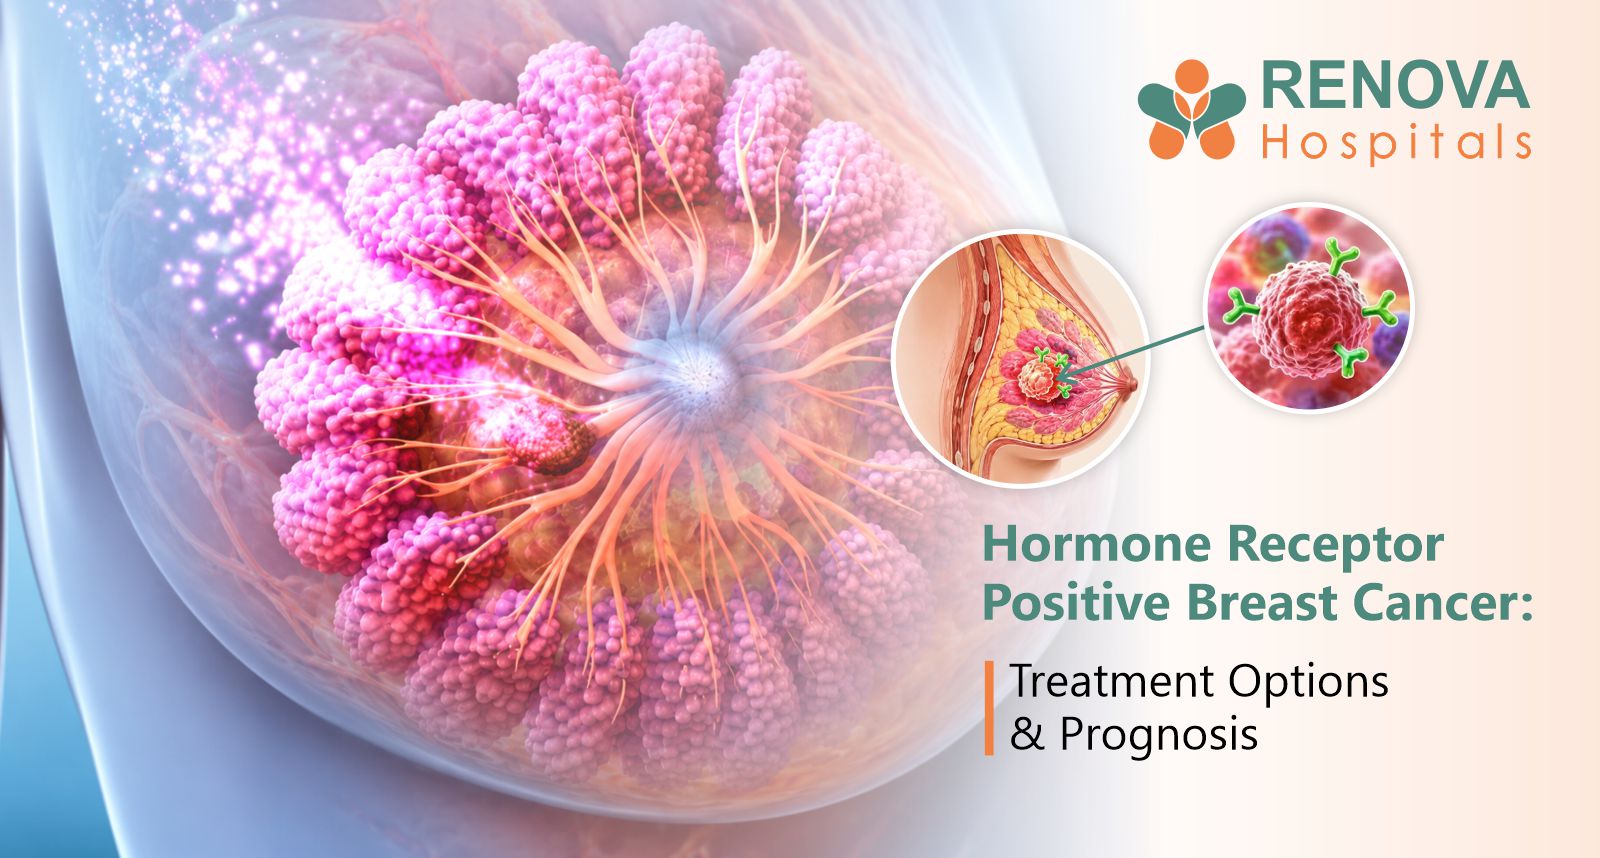
Some breast cancer cells have proteins on or inside them, called receptors, that attach to hormones circulating in the body. When a cancer has oestrogen receptors it is called ER positive, and when it has progesterone receptors it is called PR positive. A cancer with either or both is called hormone receptor positive.
In these cancers, hormones act like fuel. This is why treatments that lower hormone levels or block hormone receptors can slow or stop the cancer, and why receptor testing is one of the first steps after a diagnosis.
Is Hormone Receptor Positive Breast Cancer Common?
Yes. It is the most common type, and it is commonly cited as accounting for roughly 70 to 80 percent of newly diagnosed breast cancers.
Many of these cancers are also HER2 negative. Doctors test for HER2 as well, because HER2 status changes the treatment plan, and a cancer that is both hormone receptor positive and HER2 positive is managed differently from one that is HER2 negative.
How Is Hormone Receptor Status Tested?
Receptor status is determined by examining tissue from the tumour under the microscope, using a laboratory method called immunohistochemistry.
- A biopsy sample is taken before treatment, and a pathologist tests it for ER, PR, and HER2
- The report gives the proportion of cells that are positive and how strongly they stain
- Results are usually repeated or confirmed on the tissue removed at surgery
- In some early-stage cancers, additional genomic tests may help decide whether chemotherapy is needed alongside hormone therapy
Treatment Options for Hormone Receptor Positive Breast Cancer
Treatment is planned by considering the stage, tumour grade, HER2 status, menopausal status, and the patient's overall health and preferences. Most plans combine local treatment for the breast and underarm with systemic treatment that works throughout the body.
Surgery
- Breast conservation surgery (lumpectomy) removes the tumour and a margin of healthy tissue, while keeping the breast
- Mastectomy removes the breast, sometimes with immediate reconstruction
- Sentinel lymph node biopsy or axillary node mapping checks whether the cancer has reached the underarm lymph nodes
- The choice depends on tumour size and location, how many areas are involved, and patient preference
Renova's
Breast Oncology surgical team offers these procedures.
Dr. Amulya Chiliki, a Surgical Oncologist at Renova Hospital, Kompally, lists expertise in breast conservation surgery, nipple-areola sparing mastectomy with reconstruction, and sentinel lymph node biopsy.
Radiation Therapy
Radiation is commonly given after breast conservation surgery to lower the chance of the cancer returning in the breast, and may also be advised after mastectomy or when lymph nodes are involved. Your radiation oncologist will advise whether it is needed in your case.
Hormone (Endocrine) Therapy
Hormone therapy is the cornerstone of treatment for hormone receptor positive breast cancer. It either lowers the amount of oestrogen in the body or blocks oestrogen from acting on cancer cells.
- Tamoxifen blocks oestrogen receptors on breast cancer cells and can be used before and after menopause
- Aromatase inhibitors lower oestrogen production and are generally used in women after menopause
- Ovarian suppression may be added for premenopausal women at higher risk of recurrence
- Hormone therapy is commonly taken as a daily tablet for five to ten years, and the exact plan is individual
Chemotherapy
Chemotherapy is not needed for every hormone receptor positive cancer. It is considered when the tumour is larger, higher grade, involves lymph nodes, or has features that suggest a higher chance of recurrence, and genomic testing can help in selected early-stage cases.
Targeted Therapy
For higher-risk or advanced hormone receptor positive disease, targeted medicines may be combined with hormone therapy. These work on specific pathways that help cancer cells grow, and your medical oncologist will explain which, if any, apply to you.
Is Hormone Therapy the Same as Hormone Replacement Therapy?
No. They are essentially opposites.
Hormone therapy for breast cancer lowers oestrogen or blocks its effects to deprive the cancer of fuel, while hormone replacement therapy adds hormones to relieve menopausal symptoms. Anyone with a breast cancer history should discuss any hormone-related medicine with their oncologist before starting it.
Side Effects of Hormone Therapy
Hormone therapy is generally well tolerated, but side effects are common, and managing them well helps patients stay on treatment.
- Hot flushes, night sweats, and vaginal dryness
- Joint aches and stiffness, more common with aromatase inhibitors
- Thinning of the bones, which is monitored and can be managed
- Mood changes, fatigue, or sleep disturbance
- With tamoxifen, a small increase in the risk of blood clots and changes in the uterus, which your team will monitor
Never stop hormone therapy without speaking to your oncologist. If side effects are hard to manage, there are often adjustments or alternatives that make treatment easier.
What Is the Prognosis for Hormone Receptor Positive Breast Cancer?
The outlook for hormone receptor positive breast cancer is often favourable, particularly when it is found early, because the cancers are frequently slower growing and respond to hormone therapy. However, no single figure applies to everyone.
Factors that influence prognosis include:
- Stage at diagnosis, including tumour size and whether lymph nodes are involved
- Tumour grade and how quickly the cells are dividing
- HER2 status and other tumour features
- Age, menopausal status, and overall health
- How consistently hormone therapy is taken for the full prescribed duration
Your oncologist can share outcome information specific to your stage and tumour features, which is far more meaningful than general statistics.
Can Hormone Receptor Positive Breast Cancer Come Back?
Yes, it can, including many years after treatment.
Hormone receptor positive cancers have a recognised pattern of occasionally returning late, which is one reason hormone therapy is given for several years and follow-up continues long term. Regular check-ups, awareness of new symptoms, and completing the planned hormone therapy all help.
Living Well During and After Treatment
- Stay physically active as advised by your care team
- Maintain a healthy weight and balanced diet
- Limit alcohol and avoid tobacco
- Attend all follow-up visits and scans as scheduled
- Seek support for emotional wellbeing, which is an important part of recovery
Medical Review
Hormone receptor positive breast cancer is the most common type of breast cancer and one of the most treatable, because its reliance on hormones gives doctors effective ways to control it. Treatment typically combines surgery with hormone therapy, with radiation, chemotherapy, and targeted therapy added according to the individual's stage and tumour features.
The outlook is often favourable, particularly with early detection and consistent hormone therapy, though long-term follow-up remains important because late recurrence can occur.
Consult the Breast Cancer Team at Renova Hospitals
If you or a family member has been diagnosed with breast cancer, or you want a second opinion on a hormone receptor positive result, our oncology team can help you understand the options.
Request a consultation or call 040 2333 3333.
Questions to Ask Your Oncology Team
- What are my ER, PR, and HER2 results, and what do they mean for my plan?
- Which hormone therapy is recommended for me, and for how long?
- Do I need chemotherapy, radiation, or targeted therapy as well?
- How will side effects be managed, and how often will I be followed up?
Clear answers to these questions can help you take an active part in your treatment.
The Bottom Line
Hormone receptor positive breast cancer is the most common form of breast cancer, and its hormone dependence provides a powerful way to treat it. Most plans combine surgery with hormone therapy for several years, adding radiation, chemotherapy, or targeted therapy when the stage and tumour features call for it, and the outlook is often favourable when it is found early and treated consistently.
At Renova Hospitals, our oncology teams build an individual plan around each patient's receptor status, stage, and preferences, and stay with them through long-term follow-up.
Medical References
Medically Reviewed & Approved By
Dr. Jyosthna Elagandula
MBBS, MD, DM (Medical Oncology), DrNB (Medical Oncology), PDCR, ECMO
Senior Medical and Hemato-Oncologist, Renova Century Hospital, Banjara Hills, Hyderabad
This article has been reviewed and approved by a qualified medical professional to ensure medical accuracy and adherence to current clinical standards.